

Overview
About this procedure
Colonoscopy in Nairobi: examination of the whole colon and rectum to investigate symptoms, screen for bowel cancer and remove polyps during the same procedure.
A colonoscopy is an examination of the lining of the rectum and the whole of the colon (large bowel). A long, flexible tube carrying a high-definition camera and light is passed through the anus and advanced to the caecum, where the large bowel begins. The endoscopist sees inflammation, ulcers, bleeding points, polyps and tumours directly, can take biopsies for laboratory analysis and can remove polyps during the same procedure.
Most colorectal cancers develop from polyps over a period of years. Removing a polyp before it becomes cancerous is the main reason colonoscopy is used for screening. It is also the standard test for investigating rectal bleeding, a persistent change in bowel habit, unexplained iron-deficiency anaemia and chronic diarrhoea.
The quality of the examination depends on how well the bowel has been cleared. Written preparation instructions are given at booking and are adjusted for diabetes, kidney disease, heart disease and blood-thinning medication.
What is included
- Written bowel preparation plan
- Intravenous sedation with continuous monitoring
- Polyps removed during the same procedure
- Biopsies sent for laboratory analysis
- Written report and results consultation
- Preparation adjusted for kidney disease and diabetes
Expected outcomes
- Identification of the cause of bowel symptoms
- Removal of polyps before they can become cancerous
- Tissue diagnosis where an abnormality is found
- Detection of colorectal cancer at a stage when more treatment options are available
- A written plan for follow-up or repeat screening
Anatomical Guide
Anatomical pathway & scope orientation
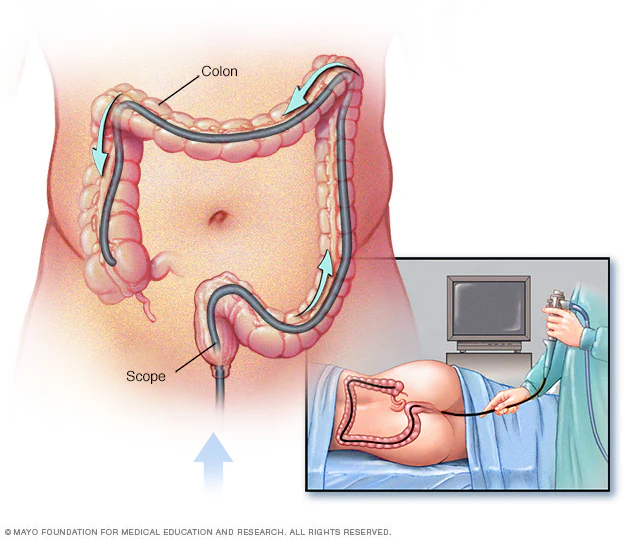
Anatomical Orientation
Colon and rectum
Anatomical pathway of the colonoscope along the rectum, sigmoid, descending, transverse and ascending colon to the caecum.
- Region
- Colon and rectum
- Examination Time
- 30-60 minutes for the examination; plan for 3-4 hours at the clinic including recovery
- Comfort Protocol
- Intravenous sedation with continuous monitoring of oxygen level, heart rate and blood pressure
Clinical Scope
Procedures we perform
Diagnostic colonoscopy
Examination of the colon and rectum to find the cause of symptoms
Screening colonoscopy
Looking for polyps and early cancer in people without symptoms
Polypectomy
Removal of polyps during the examination
Biopsy
Tissue samples sent for laboratory analysis
Surveillance colonoscopy
Follow-up after previous polyps or bowel cancer
Inflammatory bowel disease assessment
Biopsies from the bowel lining
Key benefits of this procedure
- Direct view of the lining of the entire colon and rectum
- Polyps can be removed at the same time, avoiding a second procedure
- Biopsies provide a tissue diagnosis rather than an assumption
- Screening reduces the risk of colorectal cancer by removing polyps before they become malignant
- Visual findings explained on the day; laboratory results follow
Patient Pathway
Step-by-step clinical sequence
Consultation and booking
Your doctor reviews your symptoms, medical history and medications, particularly blood thinners, iron tablets, diabetes treatment and any previous bowel tests. The procedure, its risks and sedation are explained and your consent is taken.
Bowel preparation
Follow a low-fibre diet for 1 to 2 days, take only clear fluids on the day before and take the laxative in two doses as directed on your written plan. The aim is clear, watery stool. The quality of the preparation determines the quality of the examination.
Arrival
Arrive 30 to 45 minutes early. Your identity and consent are checked, a cannula is placed in a vein for sedation and your vital signs are recorded.
The examination
You lie on your left side, sedated and monitored. The colonoscope is advanced to the caecum and the lining is examined carefully as it is withdrawn. Polyps are removed and biopsies taken as needed. The examination usually takes 30 to 60 minutes.
Recovery
You are observed for 30 to 60 minutes as the sedation wears off. The endoscopist explains the findings. Wind and mild bloating are expected. An adult must accompany you home.
Results and follow-up
Biopsy and polyp results are usually available within about a week. Your report sets out the findings and when the next colonoscopy is due, if one is needed.
Clinical Safety & Indications
Indications, risks and aftercare
When this procedure is recommended
- Rectal bleeding or blood in the stool
- Persistent change in bowel habit, including constipation or diarrhoea
- Iron-deficiency anaemia without a clear cause
- Persistent abdominal pain or bloating
- Unintentional weight loss
- Chronic diarrhoea or suspected inflammatory bowel disease
- Family history of colorectal cancer or polyps
- Positive stool blood test (FIT)
- Colorectal cancer screening from age 45 at average risk
- Follow-up of previous polyps
When it may be deferred or unsuitable
- Suspected or confirmed perforation of the bowel or peritonitis
- Severe acute colitis or toxic megacolon
- Acute diverticulitis, usually deferred until it has settled
- Suspected bowel obstruction
- Recent heart attack or unstable heart or lung disease, until stabilised
- Blood-thinning medication or a bleeding disorder that cannot be safely managed: polyp removal is deferred
- Pregnancy: deferred unless the examination is clearly essential
Recognised risks and complications
- Bloating and cramping after the procedure from the air or gas used to open the bowel; it settles within hours
- Bleeding, mainly after biopsy or polyp removal; usually minor, but it can occur up to two weeks afterwards
- Perforation (a tear in the bowel wall): rare, and more likely after polyp removal; it may require hospital admission or surgery
- Reaction to sedation, including slowed breathing or a drop in blood pressure; you are monitored throughout
- Missed lesions: no examination is perfect, and poor bowel preparation increases the chance that a polyp is missed
- Incomplete examination in some patients because of bowel anatomy or inadequate preparation; another test may then be advised
Discharge and aftercare instructions
- Rest for the remainder of the day and resume your normal diet and activities the next day unless told otherwise
- Do not drive, operate machinery, drink alcohol or sign legal documents for 24 hours after sedation
- Mild bloating and passing wind are expected; walking helps them settle
- After polyp removal, ask before restarting blood thinners or aspirin and before long-distance travel
- Seek urgent care for severe or worsening abdominal pain, a hard swollen abdomen, fever, persistent vomiting or rectal bleeding heavier than a small streak, including up to two weeks after polyp removal
- Attend your results consultation and keep the written report for future reference
Infection control & monitoring standards
- All equipment thoroughly cleaned and sterilized
- Your vital signs monitored throughout the procedure
- Emergency equipment ready if needed
- Health check and medication review before your procedure
- New disposable parts used for each patient
- Comfortable recovery room with experienced nurses
This guide provides general patient information and does not replace an individual medical consultation. Your attending doctor will explain the specific preparation, risks and alternatives relevant to your medical history.
Common Questions
Frequently asked questions
Is colonoscopy painful?
You are sedated, so most patients feel little or no discomfort and remember little of the procedure. Cramping or bloating from air in the bowel is common afterwards and settles within a few hours.
How do I prepare for a colonoscopy?
Preparation is the most important part of the test. You will receive a written plan covering a low-fibre diet, clear fluids and a split-dose laxative. Tell us if you have diabetes, kidney disease or heart disease, or if you take blood thinners, aspirin or iron, so that your plan can be adjusted.
At what age should I be screened?
For people at average risk, screening is generally recommended from age 45. If a parent, brother, sister or child has had colorectal cancer or advanced polyps, screening usually starts earlier, often 10 years before the age at which your relative was diagnosed. Your doctor will set the right starting age for you.
Which symptoms need a colonoscopy rather than screening?
Blood in the stool, a persistent change in bowel habit, unexplained iron-deficiency anaemia, unintentional weight loss and persistent abdominal pain should be investigated whatever your age. Do not wait until screening age if you have these symptoms.
Can polyps be removed during the procedure?
Yes. Most polyps are removed at the time using a wire snare or forceps passed through the colonoscope. The tissue is examined in a laboratory, and the result determines when your next colonoscopy is due.
When will I get my results?
The endoscopist explains what was seen once you have recovered. Laboratory results from biopsies or removed polyps usually take about a week and are discussed at your results consultation.
How often will I need a repeat colonoscopy?
This depends on what is found. After a normal examination in an average-risk patient, repeating the test after 10 years is common. If polyps are removed, or if you have a family history or bowel disease, a shorter interval is set by the endoscopist and written in your report.
Can I have a colonoscopy if I have kidney disease or am on dialysis?
Yes, with planning. Some bowel preparations, notably those based on sodium phosphate, can harm the kidneys and are avoided. A suitable preparation and fluid plan is chosen for you, and the procedure is scheduled around your dialysis sessions.
Do I need someone to take me home?
Yes. After sedation you must be accompanied home by an adult, and you should not drive, operate machinery, drink alcohol or sign legal documents for 24 hours.
Related Services
Other clinical services at Clarivida
Gastroenterology
Gastroscopy (OGD) & Upper Endoscopy
Direct examination of the oesophagus, stomach and duodenum
Nephrology
Comprehensive Dialysis Center
Life-Sustaining Kidney Care
Bariatric Care
Non-Surgical Gastric Balloon
Minimally Invasive Weight Loss Solution
General Medicine
General Medical Consultation
Comprehensive Primary Care & Health Checkups